

Healthcare and regulated work
Medical Billing Support Services
Medical billing support that works your claim queues from charge entry to rejections and posting, tracked by clean claim rate and days in AR.
Bought under BPO Services From $350 per agent · live in 1 weeks

A claim does not become revenue when someone finishes typing it. It must contain the authorised patient, insurance, charge and code information; survive practice and payer edits; reach the payer; receive an adjudication; and post accurately against the account.
That production line fails in narrow, repeatable places: charges arrive incomplete, avoidable errors leave the practice, clearinghouse rejections wait in a queue, or remittance data posts without the right exception review. Measuring keystrokes says nothing about whether those failures were controlled.
OveliTHub provides medical billing support services from charge entry through claim preparation and submission, clearinghouse rejection triage, secondary submission and payment posting. The team works alongside the practice’s billers, clinicians and coders. Performance is defined through accepted claims, queue age, error cause, posting control and agreed accounts-receivable measures—not visible activity.
Where the money actually leaks
Charge capture. An encounter can be documented but not reach the billing queue, reach it late, or arrive without the information the client’s coding and billing rules require. A support team can reconcile scheduled encounters to received charges and report missing items. It cannot reconstruct undocumented clinical work.
Pre-submission quality. Demographics, member identifiers, payer selection, provider data, dates, authorised codes, modifiers and claim-format fields must meet the practice and payer edit set. A scrubber can detect configured conflicts; a person must resolve the exception from authorised evidence or send it to the correct owner.
Post-submission rejection control. A claim that fails front-end or clearinghouse validation has not reached payer adjudication. Until it is corrected and resubmitted, the practice does not have a payer payment decision to post or appeal. Queue age therefore matters as much as queue volume.
These failures delay revenue and consume timely-filing time. If the underlying documentation, code assignment or insurance capture is wrong, the billing team must query the client owner rather than conceal the problem through an unsupported edit. For readers mapping the wider process, the companion guide explains where medical practices lose billing revenue.
Rejection is not denial, and the difference decides the workflow
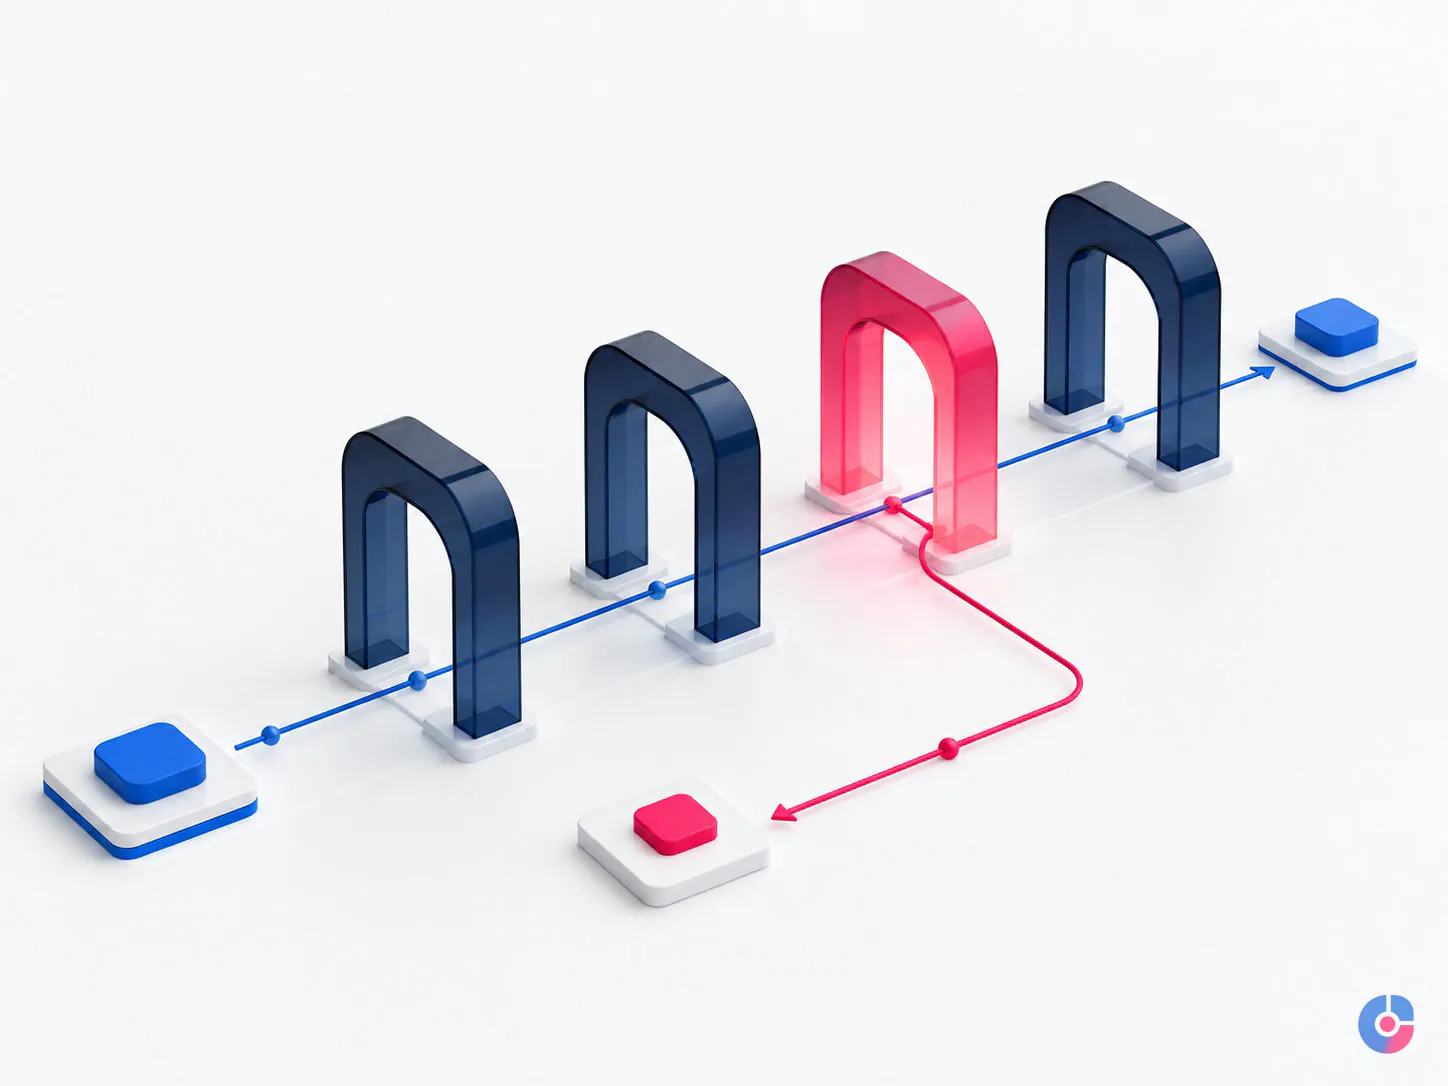
A rejection occurs before the payer adjudicates the claim. The practice, practice-management system, clearinghouse or payer front end returns it because the transaction or required data failed an edit. Examples can include an invalid member identifier, missing required field, provider mismatch, file-format problem or code combination caught by a configured rule. The action is usually to identify the source, correct authorised data and resubmit within the applicable filing window.
A denial is an adjudicated payer decision not to pay all or part of the claim as submitted. It appears through the remittance or payer response with reason and remark information. The next action may be a corrected claim, reconsideration, appeal, medical-record submission, contractual adjustment, patient responsibility, other-payer action or write-off under the client’s policy.
Putting both into one “unpaid” queue erases the clock. A rejection needs correction and resubmission. A denial may carry a payer appeal or reconsideration deadline, evidence requirement and submission route. The worklist therefore records response type, received date, filing or appeal date where known, owner, reason, next action, supporting evidence and status.
This service owns clearinghouse rejection triage within the agreed claim-production line. Deep investigation and repeated payer follow-up on older receivables belongs under AR follow-up support services.
The billing queues we work
Scope is agreed by system, location, provider, payer, claim type and work status. It can include:
- Demographic and insurance entry: enter supplied registration and coverage data, identify missing required fields and route discrepancies without performing the separate eligibility workflow.
- Charge entry: enter charges and codes supplied through the client’s authorised clinical and coding process; reconcile encounters to the expected charge source.
- Claim preparation and scrubbing: run configured edits, examine exceptions, correct administrative data supported by the record and query clinical or coding issues.
- Electronic and paper submission: create and transmit claims through approved routes, retain batch or transmission evidence and manage reports confirming acceptance or rejection.
- Clearinghouse rejection triage: classify the edit, locate the responsible source, correct within authority, resubmit and record recurring cause.
- Secondary claims: prepare and submit secondary claims using primary adjudication data and the client’s payer-specific procedure.
- Payment posting: post payment, adjustment and responsibility information from electronic remittance advice or approved paper evidence; reconcile batch and control totals.
- Patient statement preparation: prepare eligible balances and statements under client rules after insurance processing and hold checks.
Eligibility and benefit checks are handled through insurance verification support; authorisation requests belong to prior authorization support. Buyers wanting one provider across the wider chain should review revenue cycle support services.
The coding boundary is explicit
OveliTHub does not claim coding credentials and does not independently select or change diagnosis, procedure or other clinical codes. The support team works from codes supplied or approved through the practice’s clinicians and coding function.
If a configured edit detects a missing modifier, an apparent mismatch, an absent pointer or information that conflicts with the claim rule, the administrator opens a query. The query identifies the encounter, field, edit message, current source, required response, responsible clinical or coding owner and submission deadline. It does not suggest a code based on personal judgement.
Administrative corrections—such as an authorised demographic field or a transposed member identifier supported by the source record—are separated from coding and documentation changes. Each client approves a change-authority matrix before production begins. The audit trail should show who changed what, when, why and from which source.
When a payer rule or practice instruction appears inconsistent with the current system configuration, the team stops the affected item and escalates. Meeting an internal turnaround target never authorises an unsupported claim change.
The first seventy-two hours after submission need an owned worklist
Claim transmission is followed by response handling, not assumed success. Each submission batch has a control record: claim count, total charge amount where appropriate, submission time, route, file or batch identifier, response expected and assigned reviewer.
The team retrieves and reconciles available front-end, clearinghouse and payer acknowledgements on the agreed schedule. Items without the expected response become exceptions. Rejected claims enter a daily worklist with one owner and a time target determined by payer requirements and the client’s risk policy.
A practical rejection workflow is:
- confirm that the response belongs to the submitted claim and is not a duplicate transmission;
- capture the exact rejection message and originating edit layer;
- classify the cause as registration, insurance, provider, coding query, formatting, duplicate, payer configuration, system or other approved category;
- correct from an authorised source when inside the team’s authority;
- route a complete query when another owner must act;
- resubmit through the approved claim route;
- verify the new acknowledgement; and
- record completion and a root-cause candidate for repeated issues.
“Nothing sits unworked overnight” is an operating rule meaning every newly visible rejection receives review, ownership and a next action by the next scheduled work cycle. It does not promise resolution when the team waits for missing documentation, payer response, system access or a client coding decision. Blocked time is reported separately so the queue does not look artificially complete.
The numbers are defined before the baseline
Billing terms are often used as though they were universal. They are not. The client and OveliTHub agree the numerator, denominator, clock, exclusions, source and reporting lag for every measure before comparing performance.
| Measure | Working definition to agree | Questions that prevent distortion |
|---|---|---|
| Clean claim rate | Claims accepted through the defined first submission path without a correctable rejection or client-defined preventable edit, divided by eligible first submissions | Are duplicates, voids, test claims, paper claims and payer outages excluded? |
| First-pass acceptance | Eligible claims accepted by the named clearinghouse or payer gateway on initial transmission | Which acceptance layer counts, and is adjudication excluded? |
| Days in accounts receivable | Agreed receivable balance divided by the agreed average daily charge basis | Gross or net charges, which period, and which credit or non-patient balances? |
| Accounts receivable over 90 days | Agreed receivable amount aged beyond 90 days divided by total agreed receivables | From service date, billing date or another system date; with or without credits? |
| Rejection cause | First or primary rejection reason mapped to a controlled operational category | How are multi-error claims counted, and who owns the root cause? |
The baseline includes volume and mix. A month with more new patients, a payer transition or a different procedure profile cannot be compared responsibly without context. OveliTHub reports the measure and the known operational changes; it does not claim causation from a simple before-and-after view.
Queue measures add control: received, completed, rejected, resubmitted, awaiting client, awaiting payer, aging, oldest item, rework and sampled accuracy. Payment-posting control includes batch totals, unmatched payments, unapplied items, adjustment exceptions and completion evidence.

HIPAA responsibilities begin before production access
When the arrangement makes OveliTHub a business associate and the work requires protected health information (PHI), no PHI is moved and no production access is granted until the applicable service and business associate agreements are executed. The parties’ counsel and compliance owners determine the relationship and required terms.
The current HHS Office for Civil Rights business-associate guidance explains that covered entities may disclose PHI to a business associate when they obtain satisfactory assurances through a contract or other written arrangement that the information will be appropriately safeguarded. HHS also states that a BAA must define permitted and required uses and disclosures, restrict other use, address applicable Privacy Rule duties and extend relevant requirements to business-associate subcontractors.
Operational controls include named user accounts, minimum-necessary role design under the client’s policy, multi-factor authentication where supported, approved devices and locations, session timeout, prohibited local storage, secure communication, audit logging, access review, incident reporting, workforce training and documented removal. The agreement also addresses return or destruction at termination where applicable and feasible.
Offshore delivery does not remove the compliance concern; it increases the need to make data flow, location, subcontractors, access authority, supervision, logging and response paths explicit. OveliTHub does not describe a geographic location as a security control by itself.
Electronic claims and remittance follow the adopted transaction estate
The client’s clearinghouse, practice-management system and payer connections implement the applicable transaction rules. OveliTHub operates within that configured estate rather than creating its own interpretation of a standard.
CMS’s current adopted standards and operating rules page lists ASC X12N 837 Version 5010 for institutional, professional and dental health claims, and X12N 835 Version 5010-related standards for claim payment and electronic remittance advice. CMS describes an electronic remittance advice as the health plan’s explanation to a provider about a claim payment and notes the use of claim adjustment reason codes and remittance advice remark codes on its payment and remittance guidance.
The administrator does not rewrite implementation rules. They follow the client and clearinghouse procedure, preserve transmission evidence and route an unfamiliar transaction or code-set issue to the client’s billing, compliance or technical owner.
The work stays inside your practice-management environment
Where practical, the team works in the client’s practice-management, electronic health record, clearinghouse, document and payment-posting systems through approved remote access. This preserves current queues, payer configuration, role controls, timestamps, notes and audit history. Moving PHI into a parallel spreadsheet or separate database creates another record to secure and reconcile.
Remote access is configured with named accounts and the least permission needed. Copy, download, print, clipboard, USB and local storage controls follow the client’s technical design and risk decision. Screen sharing during training uses approved tools and avoids exposing unrelated patient records.
Continuity comes from documented queue procedures and cross-training, not shared credentials. At least one authorised backup learns each material queue. Payer notes record the issue, source, effective or observed date, affected workflow, approved instruction, owner and next review. When a person leaves, access is removed on the agreed timetable while the worklist, notes and evidence remain in the client-controlled system.

The first four weeks establish a baseline before scale
- Week one: map and observe. Confirm entities, locations, providers, systems, clearinghouse, payers, claim types, queues, access, BAA status and decision owners. Shadow current work without moving the entire production line.
- Week two: document and define. Write task procedures, payer-specific notes, authority boundaries, escalation routes and metric formulas. Take the available baseline with data limitations stated.
- Week three: run a bounded queue. Move one agreed work type or payer group, review every item or a risk-based sample and compare batch and response evidence.
- Week four: stabilise and decide. Examine acceptance, rejection cause, queue age, rework, client dependencies and posting exceptions. Correct the procedure before adding the next queue.
A medical billing back-office team should not receive every payer and queue on day one. Staged transfer protects revenue, makes training gaps visible and prevents old backlog from being mistaken for new-team performance.
What we cannot fix, and who must
Clinical documentation stays with the clinician and the client’s clinical governance process. The team reports a missing or conflicting element; it does not add it.
Code selection and coding policy stay with the client’s authorised coders and responsible professionals. OveliTHub submits a precise query and waits for an approved response.
Front-desk capture—identity, insurance card, demographic and referral inputs—remains a client process unless separately transferred. Repeated registration-related rejections are grouped and returned with examples so the front end can correct the source.
Payer contracts and enrolment stay with the authorised client owners. The team can flag a rate, provider or participation issue but does not interpret contract entitlement.
Patient financial and write-off policy stays with the practice. Adjustments and statements are prepared only under approved rules and access.
The escalation is operational: claim identifier, issue, exact source or response, action already taken, required owner, deadline, financial or filing risk, and work status. “Need help” is not a complete billing query.
The claims workflow review returns a measurable pilot plan
The review examines charge arrival, pre-submission edits, transmission evidence, clearinghouse responses, correction ownership, secondary flow, remittance posting, system roles, payer notes and reporting definitions. It samples the current process without representing the sample as a full audit.
You receive a queue map, agreed metric dictionary, available baseline, top observed rejection categories, dependency and coding-query map, access-control questions, proposed first pilot queue and the conditions required before production transfer.
A pilot has a named population, dates, starting backlog rule, completion standard, review sample and stop conditions. It compares process measures without promising a collection outcome controlled by documentation, coding, payer adjudication or contract terms.
Review the claim line before moving the queue
Start with current acceptance evidence, rejection worklists, payment-posting controls and metric definitions. OveliTHub will show which queue can move safely and what the client must fix first.
Request a claims workflow review, email support@ovelit.com, or call +880 1707-510532. Browse all digital services for adjacent healthcare support.
Set at the service, not here
The terms every BPO services engagement runs on
The price, the ownership and the renewal terms are the same whichever offering you buy, which is why they are published once rather than restated on every page.
- Starting price
- From $350 per agent per month, in US dollars. 4 hours a day, 5 days a week, one channel, documented SOPs and a monthly QA report. Live in 2 weeks
- Channels
- Email, live chat, phone, social inboxes, CRM and back-office systems
- Coverage
- Hours are stated per desk and written into the agreement, including which of your working days are covered from UTC+6
- Data protection
- UK GDPR Article 28 processor agreement, Standard Contractual Clauses and the UK IDTA where data leaves the UK or EEA
- Quality
- Monthly QA scoring against a rubric you approve, with the sampled tickets attached
- Tooling
- We work inside your helpdesk and your CRM. No forced migration to a platform we own
Which practice-management systems do you support?
System fit is confirmed during scoping against the client’s version, modules, clearinghouse connection, roles and remote-access method. Familiarity with a product name is not treated as permission to bypass the client’s configuration or training.
Is there a minimum claim volume?
The practical minimum depends on claim mix, number of payers and providers, coverage hours, queue fragmentation and reporting burden. OveliTHub scopes the pilot from actual monthly work rather than publishing a universal threshold.
How is the baseline measured?
The parties define the population, source, formula, dates, exclusions and known data limitations in writing. The baseline is taken before the pilot queue moves and is segmented where payer or claim mix materially differs.
Who owns the payer notes when the engagement ends?
The client owns the client-specific workflow documentation and payer notes produced for the service, subject to the agreement. They remain in or are handed over to the approved client workspace, with access removed according to offboarding terms.
Do you assign medical codes?
No. OveliTHub works from codes supplied or approved by the practice’s authorised clinical and coding process. Potential mismatches become documented queries.
Can we hire one billing person instead?
Yes. Practices that want a single embedded person under their direct workflow may prefer a remote medical billing assistant . This service is structured around defined claim-production queues and shared controls.
Bought together
Also in healthcare and regulated work
AR Follow Up Support Services for Practices
Trained AR specialists working aged claims by bucket and denial reason. Reduce days in AR and recover revenue that is quietly sitting…
What it coversMedical Records Management Support
Records support that indexes charts, prepares them for clinic and releases them inside the legal window, with an audit trail on every…
What it coversPatient Scheduling Support Services
Scheduling support that confirms, reminds, backfills cancellations from a waitlist and works recall lists, so clinic hours stay full and get paid.
What it coversNext step
Tell us what you need from Medical Billing Support Services
Volume, hours and the systems it has to run in. The first reply carries a scope and a figure rather than a request for the basics.
- You send the brief A few lines is enough. No form fields you have to guess at.
- We reply in one business day With questions if we have them, and a range if we do not.
- You decide, not us No retainer to talk. If it is not our work, we say so.
Ask about Medical Billing Support Services
Priced per agent per month. The written procedure comes before the first agent is hired, so say what the work actually is.
We use what you send to answer you. We do not sell it, and we do not add you to a list.